
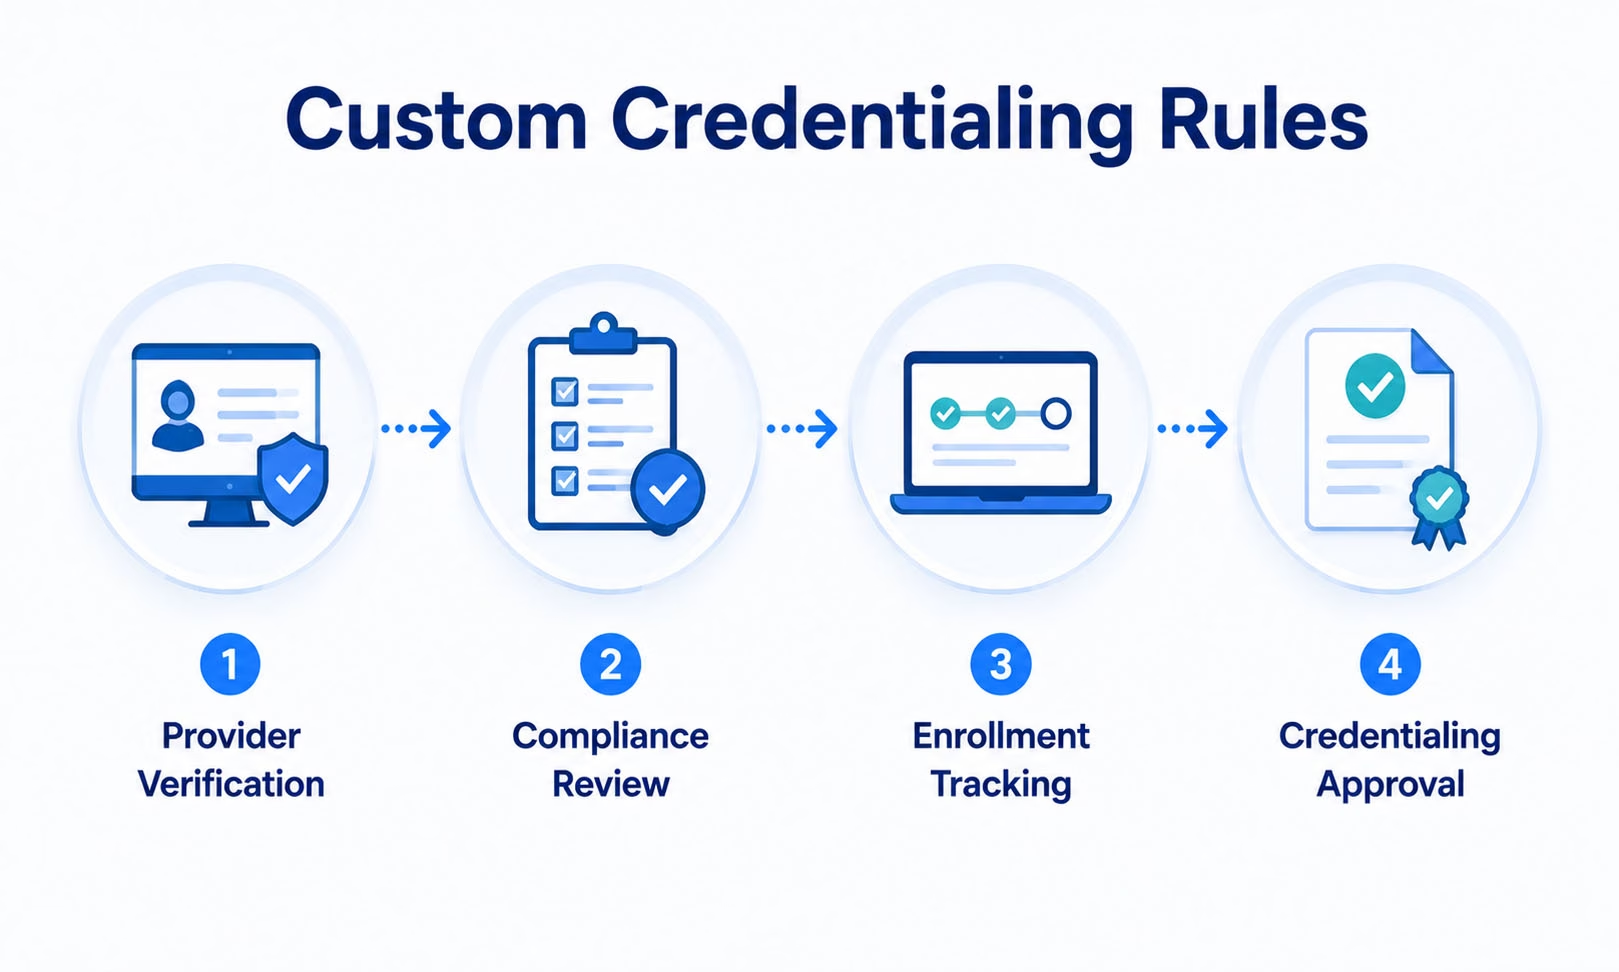
Payer-specific credentialing requirements are the additional rules, documents, participation criteria, and workflows that can differ by health plan, network, product, state, provider type, and practice arrangement. The best way to manage these differences is to maintain a payer rules matrix that records each requirement, its source, effective date, applicability, and last verification date.
Healthcare credentialing becomes difficult when teams assume that one completed provider file will satisfy every payer.
Much of the underlying provider information may be the same.
However, different payers may apply different requirements or processes across areas such as:
- Credentialing applications
- Primary source verification
- Board certification
- Work history
- Professional liability information
- CAQH
- Group affiliation
- Practice locations
- Network products
- Enrollment
These differences are why one standardized provider file may not satisfy every payer, network, or product.
The solution is not to memorize every rule.
The solution is to maintain a controlled payer-specific requirements system.
What Are Payer-Specific Credentialing Requirements?
Payer-specific credentialing requirements are the rules an individual payer or credentialing organization applies when evaluating a practitioner for participation.
These requirements may exist alongside broader credentialing standards such as NCQA requirements.
Depending on the payer, differences can involve:
- Application method
- Required provider documents
- CAQH use
- Board certification criteria
- Work-history review
- Professional liability information
- Peer references
- Credentialing committee review
- Recredentialing
- Ongoing monitoring
Does NCQA Mean Every Payer Uses the Same Credentialing Rules?
No.
NCQA establishes a credentialing framework for applicable accredited organizations.
Its requirements address areas such as:
- Credentialing policies
- Primary or recognized-source verification
- Credentialing committee review
- Recredentialing
- Ongoing monitoring
- Practitioner appeal rights
That does not mean every health plan has an identical application, network, product, or participation policy.
Credentialing Rules and Enrollment Rules Should Be Separated
One of the biggest causes of confusion is putting every payer requirement into the credentialing bucket.
| Credentialing Requirement | Enrollment or Contracting Requirement |
|---|---|
| License verification | Group TIN |
| Board certification review | Practice location setup |
| Work history | Provider-to-group affiliation |
| Professional liability review | Contract execution |
| Sanction monitoring | Network product activation |
| Credentialing committee decision | Effective date |
A payer may request both types of information during the same onboarding process, but they serve different purposes.
Why Payer Rules Differ
Different organizations operate under different:
- Health plan policies
- Accreditation frameworks
- State requirements
- Government-program rules
- Network structures
- Products
- Provider contracts
This is why the same provider can have different requirements with two payers.
Build a Payer Rules Matrix
A payer rules matrix should become the operational source of truth for payer-specific requirements.
At minimum, track:
| Field | What to Record |
|---|---|
| Payer | Health plan or credentialing entity |
| State | Applicable state or market |
| Product | Commercial, MA, Medicaid, exchange, or other product |
| Provider type | MD, DO, NP, PA, behavioral health, facility, etc. |
| Requirement | Exact rule or required item |
| Category | Credentialing, enrollment, contracting, affiliation, or location |
| Source | Portal, manual, contract, email, bulletin, or representative |
| Effective date | Date the rule became applicable if known |
| Last verified | Date staff confirmed the requirement |
| Owner | Person responsible for maintaining the rule |
Why the Source of the Rule Matters
A payer rule should not exist in the tracker simply because someone remembers hearing it.
Record where it came from.
Useful sources can include:
- Payer provider manual
- Credentialing policy
- Provider portal
- Application instructions
- Contract
- State Medicaid guidance
- Payer bulletin
- Written correspondence
Telephone guidance can also be useful operationally, but the tracker should record the date, representative, reference number, and what was said.
Add a “Last Verified” Date to Every Payer Rule
Payer requirements change.
Without a verification date, staff may continue applying a rule that was accurate two years ago but is no longer current.
For each payer-specific requirement, record:
- Date added
- Last verified date
- Source
- Staff member who verified it
This creates a controlled operational knowledge base.
Separate Rules by State
A national payer brand may not operate identically in every state.
Requirements can differ because of:
- State regulation
- Regional health-plan entities
- Medicaid contracts
- Local network structure
- Product availability
A payer rules matrix should therefore avoid one universal row labeled simply “Payer A.”
Separate Rules by Product
The same payer can offer multiple products.
Examples include:
- Commercial PPO
- Commercial HMO
- Medicare Advantage
- Medicaid managed care
- Exchange plans
A provider’s credentialing or network status in one product should not automatically be assumed to apply to another.
Separate Rules by Provider Type
Payer requirements may differ for:
- Physicians
- Nurse practitioners
- Physician assistants
- Psychologists
- LCSWs
- Therapists
- Facilities
- Laboratories
This is especially important when the organization manages multi-specialty practices.
How Should CAQH Be Represented in the Payer Rules Matrix?
CAQH Provider Data allows providers to maintain professional and practice information and authorize participating organizations to access it.
More than 1,000 health plans and healthcare organizations use the platform for credentialing and related purposes.
However, CAQH use should still be tracked payer by payer.
Record whether the payer:
- Uses CAQH
- Requires a completed CAQH profile
- Requires direct portal submission in addition to CAQH
- Requests additional supporting documents
See our CAQH Provider Data Portal guide for the broader CAQH workflow.
Does CAQH Eliminate Payer-Specific Requirements?
No.
CAQH reduces duplicate provider-data collection by allowing providers to maintain one profile that can be shared with authorized organizations.
The payer still applies its own credentialing and participation process.
A complete CAQH profile therefore does not mean:
- Credentialing is approved
- Network participation is approved
- Enrollment is complete
- The group affiliation is active
- The provider can bill immediately
Why Medicaid Rules Need Their Own Section
Medicaid managed care is particularly important because federal rules interact with state requirements.
CMS requires states to establish a uniform credentialing and recredentialing policy for managed care network providers.
Managed care plans must follow that state policy.
States may also establish additional provider-selection requirements.
That means a Medicaid credentialing rule should be documented with:
- State
- Medicaid program
- MCO
- Provider type
- Requirement source
Medicaid Enrollment and MCO Credentialing Are Separate
CMS distinguishes Medicaid screening and enrollment from managed care credentialing.
State enrollment determines whether the provider is enrolled in the Medicaid program.
The managed care organization may separately determine whether the provider meets its network credentialing requirements.
A provider can therefore be enrolled with the state and still not be participating with a specific Medicaid managed care plan.
Can a Medicaid Plan Have Additional Provider-Selection Criteria?
Yes, within applicable law and state requirements.
CMS guidance recognizes that a managed care plan may decline to enter into a network provider agreement with a provider who passed state screening and enrollment but did not satisfy the plan’s network credentialing criteria.
This is another reason credentialing status and Medicaid enrollment status should be tracked separately.
How Should Board Certification Rules Be Tracked?
Do not create one universal rule that every payer requires board certification.
Instead, document:
- Payer
- Provider specialty
- Whether board certification is required
- Whether board eligibility is accepted
- Any timeframe or exception
- Source of the requirement
This prevents staff from applying one payer’s policy to another.
How Should Work-History Requirements Be Tracked?
Payers may request work history as part of credentialing.
The operational question is not simply whether a CV exists.
Track:
- Required history period
- Whether gaps require explanation
- How gaps should be documented
- Whether the payer uses CAQH work history
Do not invent a universal gap threshold unless the applicable payer or credentialing standard provides one.
How Should Professional Liability Requirements Be Tracked?
Different organizations may have different requirements for professional liability coverage.
The payer-rules matrix can record:
- Whether coverage is required
- Required limits where specified
- Whether self-insured arrangements are accepted
- Required supporting documentation
Do not assume every provider or payer uses the same liability requirement.
How Should Sanction and Exclusion Requirements Be Managed?
Credentialing organizations may conduct ongoing monitoring for sanctions and other issues.
NCQA’s full-scope credentialing framework includes monitoring practitioner sanctions, complaints, and quality issues between recredentialing cycles.
Practices should distinguish:
- Routine credentialing monitoring
- Government exclusion screening
- Payer-specific requests
- Employer background checks
These are not necessarily the same process.
What Is a Payer Exception?
A payer exception is a provider situation that does not fit the ordinary workflow.
Examples can include:
- Work-history discrepancy
- Board-certification issue
- Professional liability question
- License restriction
- Sanction match requiring clarification
- Provider type not accepted under the intended product
The correct response is to create an exception record rather than rewriting the general payer rule around one unusual case.
Create an Exception Log
| Provider | Payer | Issue | Source | Resolution |
|---|---|---|---|---|
| Provider A | Payer 1 | Work-history clarification requested | Portal request | Provider response submitted |
| Provider B | Payer 2 | Board-certification question | Written payer request | Pending review |
This preserves the difference between a general payer requirement and a provider-specific exception.
Do Not Convert One Payer Representative’s Answer Into a Permanent Rule
Payer representatives can provide useful operational guidance.
However, a verbal answer should not automatically become a permanent organization-wide credentialing policy.
Where possible:
- Record the call reference number.
- Record the representative’s name or ID.
- Record the date.
- Request written confirmation for unusual requirements.
- Compare the answer with current payer documentation.
Use Version Control for Payer Rules
Do not simply overwrite old requirements.
When a payer changes a rule, preserve:
- Previous requirement
- New requirement
- Effective date
- Source
- Date staff updated the tracker
This is especially useful when reviewing older applications or disputes about which rule applied at the time.
How Often Should Payer Rules Be Reviewed?
There is no universal review interval.
Higher-risk requirements may deserve more frequent verification.
Trigger a review when:
- A payer publishes a new provider manual
- A portal changes
- A state Medicaid contract changes
- The organization adds a new product
- A payer begins requesting information not listed in the matrix
- Multiple applications encounter the same new issue
What Should Credentialing Staff See Before Starting an Application?
Before beginning payer work, staff should be able to see:
- Payer
- State
- Product
- Provider type
- Credentialing requirements
- Enrollment requirements
- Contracting status
- Location requirements
- CAQH requirements
- Source and last verification date
This reduces dependence on tribal knowledge.
How Should Credentialing and Billing Share Payer Rules?
Credentialing and billing need different parts of the payer relationship.
Credentialing should communicate confirmed operational facts such as:
- Provider approved
- Group affiliation active
- Location active
- Product active
- Effective date
- Any known participation restriction
Billing should not need to interpret raw credentialing notes or incomplete payer applications.
Payer Rules Matrix Checklist
- Identify the payer.
- Identify the state.
- Identify the product.
- Identify provider type.
- Separate credentialing from enrollment.
- Separate enrollment from contracting.
- Document CAQH use.
- Document required credentials.
- Document payer-specific exceptions.
- Record the authoritative source.
- Record the effective date when available.
- Record the last verification date.
- Assign an owner.
- Preserve previous rule versions.
- Maintain provider-specific exceptions separately.
Frequently Asked Questions
What are payer-specific credentialing requirements?
They are credentialing rules and participation criteria that vary by payer, network, product, state, provider type, or practice arrangement.
Does NCQA require every payer to use the same credentialing criteria?
No. NCQA establishes credentialing standards and process requirements for applicable accredited organizations, but individual health plans can still have different participation policies and operational requirements.
Is a W-9 a credentialing requirement?
Usually it is better classified as enrollment, tax, contracting, or organizational information rather than a professional credentialing qualification.
Does a complete CAQH profile satisfy every payer?
No. CAQH standardizes provider data sharing, but individual payers still apply their own credentialing and participation requirements.
Can a provider be enrolled in Medicaid but not credentialed with the Medicaid MCO?
Yes. CMS distinguishes state screening and enrollment from managed care plan credentialing and network participation.
Can the same payer have different requirements in different states?
Yes. Requirements may differ because of state regulation, Medicaid contracts, regional plan structure, products, and network policies.
Should a payer rule be stored without a source?
Ideally, no. Store the source and date so staff can verify whether the rule remains current.
What should happen when a payer representative gives a new requirement?
Document the call, obtain a reference number, seek written confirmation where possible, and determine whether it is a general payer rule or a provider-specific exception.
What is the best way to manage payer-specific requirements?
Use a payer rules matrix organized by payer, state, product, provider type, requirement category, source, effective date, owner, and last verification date.
Turn Payer Knowledge Into Controlled Operational Data
Payer-specific credentialing should not depend on one employee remembering how a plan handled the last application.
A mature credentialing operation converts payer knowledge into structured data.
For every important rule, the organization should know:
- Who requires it
- Which state it applies to
- Which product it applies to
- Which providers it applies to
- Whether it is credentialing, enrollment, or contracting
- Where the requirement came from
- When it was last verified
This makes payer-specific knowledge easier to scale across multiple providers, practices, states, and credentialing staff.
eClinicAssist supports healthcare organizations with payer-specific enrollment tracking, provider and facility records, document management, credentialing task workflows, follow-up dates, payer status tracking, group affiliations, approvals, effective dates, and related credentialing administration.
eClinicAssist does not create payer requirements, make payer credentialing decisions, guarantee network participation, or guarantee reimbursement.
Contact eClinicAssist to discuss credentialing and payer enrollment workflow management for your organization.
This article provides general administrative information and is not legal, credentialing, accreditation, Medicaid, Medicare, or payer-specific advice. Health-plan requirements vary by payer, state, product, provider type, network, and contract and may change over time. Verify current requirements directly with the applicable payer, state Medicaid agency, government program, or credentialing organization.





